
Health
Is Baby Formula Safe? The FDA Just Released Its Biggest Test Results Ever

Parents worry. That is just what parents do. And for the last couple of years, a lot of that worry has been pointed directly at infant formula — the stuff millions of babies eat every single day when breastfeeding is not an option.
On April 29, 2026, the FDA gave parents the most detailed answers to those questions that any government agency has ever produced. They tested more than 300 samples of commercial infant formula sold in stores across the country. Sixteen brands. Hundreds of individual products — powders, ready-to-feed liquids, concentrated liquids. More than 120,000 separate data points run through FDA laboratories.
What Got Tested and Why It Took This Long
Operation Stork Speed had a long backstory before anyone gave it a name. Parents have been asking what was in infant formula for years — not in a paranoid way, just in the way any reasonable person asks what their newborn is eating three times a day. And the answers they got back were vague at best. Marketing language. Reassurances that did not point to any actual data. A lot of people trust us without much to back it up. That gets old fast when you are talking about a baby. Pediatricians pushed. Consumer groups pushed. Nobody moved fast enough.
Then Consumer Reports published an investigation in 2024 that named names — specific brands, specific chemicals, specific numbers. Heavy metals. Concerning levels. It landed like a grenade in parenting communities online. Suddenly, it was not an abstract worry anymore. It was a chart with familiar brand names on it. Parents who had no other option but formula were now reading that the product their baby depended on might have something in it that should not be there. Some of them stopped buying it. Doctors had to talk families off ledges and back toward feeding their kids.
That is when the Trump administration launched Operation Stork Strike in March 2025. Not because the government suddenly developed a conscience about infant nutrition, but because the pressure had built to a point where doing nothing was no longer a defensible position. The story spread fast. Some families read it and stopped buying formula altogether — even in cases where formula was the only thing keeping their baby fed. That kind of fear, whether warranted or not, has real consequences.
So the FDA went to work. Their lab tested each sample for lead, mercury, cadmium, arsenic, pesticides including glyphosate and glufosinate, PFAS compounds — the synthetic chemicals people call “forever chemicals” — and phthalates, which are plastics-related chemicals that can seep into food from packaging and manufacturing equipment. They ran the samples through every major category of concern that researchers and parents had raised, and then they published everything.
The Results, Broken Down Honestly
On heavy metals, the results were about as good as you could hope for. Lead, mercury, cadmium, and arsenic all came back below the limits the EPA sets for drinking water — and not just in most samples. In all of them. Dr. Steven Abrams, a pediatrics professor at the University of Texas at Austin who looked over the data, came out and said plainly that there is no reason not to use any formula currently available in the U.S. For a researcher who studies this stuff professionally to say that clearly is worth something. Pesticides were
essentially a clean sweep. Ninety-nine percent of all samples showed zero detectable pesticides. That number is hard to argue with.
PFAS is where it gets a little more complicated. The FDA tested for 30 different PFAS compounds. Twenty-five of them showed up as undetected across the board. Five were found in at least some samples. The concentrations varied, but the FDA reported that 95 percent of all samples fell at or below 28 parts per trillion. The EPA’s current limit for drinking water sits at 4 parts per trillion for the most common PFAS types, PFOA and PFOS. A chunk of the formula samples came in above that water standard, even while staying within the 28 ppt range the FDA cited.
That gap is real, and it matters, even if it does not mean the formula is dangerous.
The Scientists Who Said — Not So Fast
Kyle Diamantas, the FDA’s Deputy Commissioner for Foods, called the results encouraging and said they reinforce that formula is a safe choice for families who depend on it. RFK Jr., the Health and Human Services Secretary, issued a statement saying that even small exposures matter for newborns and that manufacturers will be held accountable.
Some independent researchers took a more cautious tone.
Dr. Sheela Sathyanarayana, a professor of pediatrics at UW Medicine and the Seattle Children’s Research Institute, said something that’s really important to think about. Heavy metals, such as lead and arsenic, are found naturally in the soil and water. These heavy metals, like lead and arsenic, are also found in the food we eat. Only in very small amounts. This is because the earth is not a clean place, and farming happens outside in the real world, where these heavy metals, like lead and arsenic, are present. Just because we find these metals, like lead and arsenic, in small amounts in our food, it does not mean they are safe, but it helps us understand why they are there in the first place.
PFAS is a completely different category. These chemicals were invented in labs. Nobody puts PFAS in baby formula on purpose. That is the thing. These chemicals got there because they spent decades soaking into everything — the water, the soil, the air near factories, the lining of food packaging, the equipment used in processing plants. They were useful. Industry loved them. They made things waterproof, non-stick, and heat-resistant. And for a long time, nobody was asking hard questions about where they were ending up. Now we know. They ended up everywhere. Including, apparently, in cans of infant formula sitting on store shelves.
This is not a manufacturing scandal in the traditional sense. No company dumped PFAS directly into baby food. But the fact that these chemicals traveled so far through the environment that they showed up in a product designed for newborns — that tells you something about the scale of the problem. You cannot factory-inspect your way out of contamination that is already baked into the water table and the soil where crops grow. The source is not one bad actor. The source is forty years of industrial use, and not nearly enough regulation about where any of it was going.
Her concern was not that parents should panic. It was that the detection of fully synthetic chemicals in baby food is a problem worth taking seriously — not just in formula, but across the entire U.S. food system.
Brian Ronholm at Consumer Reports pushed on a different issue. The U.S. still does not have official legal limits for how much of any of these contaminants is allowed in infant formula. Right now, there is no enforceable ceiling. The FDA says it is developing action levels, and Kyle Diamantas confirmed the agency is working toward that. But until those numbers are written into actual policy and manufacturers are legally required to meet them, the testing is informative without being binding.
Where Things Go From Here
The FDA was upfront about the fact that this was a starting point, not a finish line. More testing is coming. Products that hit the market after this survey closed will be tested too. Secretary Kennedy is scheduled to meet with the heads of major formula companies on May 2026 to talk through what modernizing oversight looks like going forward.
Abbott, one of the largest formula manufacturers in the country, came out in support of the FDA establishing real science-based limits. Its spokesperson called producing formula at scale in the U.S. a matter of national security — a phrase that reflects just how raw the memory of the 2022 formula shortage still is for a lot of people in the industry.
Dr. Abrams recommended that the FDA expand future testing to include organic formulas, imported brands, and goat’s milk-based options — categories not fully covered in this first round. He also called for the agency to set up a regular reporting schedule so parents are not left waiting years between updates.
What parents have right now is this: the most comprehensive safety check of U.S. infant formula ever completed, and a result that says the formula your baby is drinking cleared every major test. That is real progress. At the same time, the scientists closest to this work are saying clearly that finding synthetic chemicals in infant formula at any concentration is not something to quietly accept as normal — and that the rules governing what is allowed in baby formula are long overdue.
Health
Health Insurance, Mental Health & Healthcare: Why They’re All Connected

Let’s face it. Most of us ignore health insurance until we have to use it. It’s easier to worry about the reason we’re at the doctor in the first place than to find the time to unravel health insurance lingo.
By then, it’s already stressful enough without trying to decode confusing insurance terms too.
So here’s a simple, no-jargon guide to how health insurance, mental health care, and everyday healthcare actually connect — and a few small habits that can save you money, time, and a whole lot of anxiety.
Why Health Insurance Is More Than a “Just in Case” Plan
Most people treat insurance like a safety net they hope to never use. But a good plan isn’t just about emergencies — it’s about everyday access.
Here’s what it really covers, in plain terms:
- Premium – the amount you pay every month just to stay covered
- Deductible – what you pay out-of-pocket before insurance starts helping
- Copay – a fixed fee you pay for a visit or prescription
- Out-of-pocket maximum – the most you’ll pay in a year before insurance covers 100%

Understanding the basics of your health insurance coverage
Knowing these four terms alone can change how you use your plan. A lot of people skip checkups simply because they assume insurance won’t help — when in many cases, preventive visits are fully covered, including screenings that support things like heart health.
Quick tip: Call your provider once a year and ask, “What’s fully covered under my plan right now?” Coverage details change more often than people realize.
Mental Health Is Health — Insurance Is Finally Catching Up
For years, mental health care was treated like an extra — something separate from “real” medical care. That’s changing, slowly but surely.
Here’s what’s shifting:
- More insurance plans now include therapy and counseling sessions
- Teletherapy is increasingly covered, making it easier to fit into a busy schedule
- Some employers offer Employee Assistance Programs (EAPs) with free short-term counseling
- Mental health screenings are being added to routine check-ups

Mental health is part of overall wellness, not separate from it
Still, coverage varies a lot depending on your plan and location, so it’s worth checking:
- Does my plan cover in-network therapists?
- How many sessions are covered per year?
- Is online/virtual therapy included?
If cost is still a barrier, community mental health centers and sliding-scale therapy options are worth exploring — many are more affordable than people expect.
A gentle reminder: Needing support for your mental health isn’t a weakness. It’s simply another form of healthcare — the same as treating a sprained ankle or a fever.
Getting the Most Out of Everyday Healthcare
Healthcare isn’t just hospitals and emergencies. It’s the small, consistent habits that keep you out of the ER in the first place.
A few things that make a real difference:
- Book your annual physical — even when you feel fine
- Keep a simple health folder — past prescriptions, test results, and allergies in one place
- Use in-network providers whenever possible to avoid surprise bills
- Ask about generic medications — they’re often just as effective and far cheaper
- Track your symptoms before appointments so nothing gets forgotten in a rushed 10-minute visit
A simple healthcare checklist worth keeping on hand
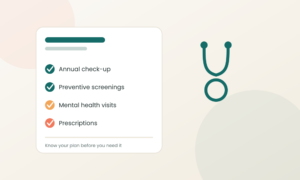
Small habits like these don’t just save money — they help doctors catch potential issues earlier, when they’re easier (and cheaper) to treat.
Bringing It All Together
Health insurance, mental health care, and everyday healthcare aren’t three separate boxes — they’re all part of the same picture: taking care of yourself before small issues become big ones.
A few final takeaways:
- Review your insurance plan at least once a year — don’t just renew on autopilot
- Ask directly about mental health coverage; don’t assume it isn’t included
- Use preventive care — it’s often free and can save you from bigger costs later
- Keep your health records organized so you’re never starting from scratch at a new appointment
Take care of your health gradually. Booking a check-up for the first time might seem like a daunting task, but calling your insurance or asking your employer for mental health coverage are great simple steps and greatly benefit your life in many ways. There are many tips in our healthy life guide that can help you take on more healthy habits one at a time.
Disclaimer: This article is not directed to provide any medical or financial advice. Always reach out to your insurance or a medical professional for information that specifically pertains to you.
Health
A New Hope for One of the Deadliest Cancers: Pancreatic Cancer Breakthroughs in 2026
For decades, a diagnosis of pancreatic cancer felt like a death sentence. Doctors would deliver the news, and most patients — and their families — had little reason to feel hopeful. Today only about 13% of people who have pancreatic cancer are still alive five years later. If you compare that to other kinds of cancer you will see that the number of people who survive has gone up a lot because we have better treatments and we can find cancer sooner. Pancreatic cancer has not been getting better like other cancers have.. Now things might be getting better for people, with pancreatic cancer.
In May 2026 the doctors and the scientists have a lot to be happy about. They have found a drug called daraxonrasib that is really working. They also have a vaccine that is made just for this disease.. They have a device that uses electric fields to fight the disease. All of these things are giving people hope. For people like Vicky Stinson, who’s a 65 year old lady from Flagstaff, Arizona and used to design landscapes these new discoveries are very important. The disease is very bad. Now Vicky Stinson and other patients like her have something to be hopeful, about. The new drug daraxonrasib and the built vaccine are really making a difference.
Why Is Pancreatic Cancer So Hard to Fight?
To understand why these new treatments for cancer matter so much you first have to understand why pancreatic cancer is so difficult to deal with.Pancreatic cancer is difficult to deal with because the pancreas is an organ that is tucked behind many other organs in your abdomen.The pancreas is hard to find because of where it sits so it is nearly impossible to feel or see the pancreas during a checkup.When a patient notices something is wrong with their body, like some stomach pain or difficulty eating or they get sudden-onset diabetes the pancreatic cancer has usually already spread to other parts of the body.This is a problem because roughly 80 percent of patients are diagnosed with pancreatic cancer at a late stage when the pancreatic cancer is much harder to treat.
Even when doctors detect the cancer, treating it is a nightmare. These tumors build what one doctor describes as a “cocoon” around themselves — a thick protective layer that stops chemotherapy drugs from getting through. On top of that, the pancreas sits right next to the body’s major blood vessels. As oncologist Dr. Arif Kamal of the American Cancer Society explains, those vessels are like highways for the body. If cancer cells escape from the pancreas, they can travel quickly to other parts of the body. And unlike many other cancers that form solid, contained masses, pancreatic cancer cells tend to scatter easily — like a handful of sand, not a tennis ball. You simply cannot catch every grain.
The Pill That Is Changing Everything: Daraxonrasib
Now, a drug called daraxonrasib, developed by a company called Revolution Medicines, is turning heads across the medical world.The drug works by targeting a specific gene mutation found in most pancreatic cancers. This mutation, known as KRAS, acts like a broken traffic light stuck on green — it keeps sending signals for cancer cells to divide and grow without stopping. Daraxonrasib essentially locks that broken signal off, causing the cancer cells to slow down or stop growing altogether.
In a large Phase 3 clinical trial called RASolute 302, patients who took daraxonrasib — just one pill a day — lived an average of 13.2 months. Patients who received standard chemotherapy lived only 6.7 months on average. That means the new drug roughly doubled how long patients survived. In a disease where every extra month matters enormously to families, that is a stunning result.
This is really exciting because of the way patients took the medication. The thing about chemotherapy is that it usually means spending a lot of time at a hospital or clinic where you are connected to a drip with a tube, for hours.Daraxonrasib is a simple once-a-day pill taken at home. Patients in the trial reported far fewer brutal side effects than those on chemotherapy, and none of them dropped out of the trial because of side effects.
Vicky Stinson was one of the people who took this drug as part of an earlier clinical trial. She described her 13 months on daraxonrasib as “a full year of normalcy.” She hiked the Dolomite mountains in Italy. She kept up with her exercise classes. Her biggest complaint? A bit of acne on her face and neck — which, she joked, “brought her back to her teens.”
Because the results look really good the U.S. Food and Drug Administration has already let the drug be given to patients even before it gets full approval.Doctors and cancer experts are trying to figure out how to get it to patients.
A Vaccine Built Just for You
Daraxonrasib is not the only exciting development. Scientists are working on a kind of vaccine. This vaccine does not prevent diseases. Instead the cancer vaccine fights cancer that’s already in the body. The cancer vaccine uses mRNA technology. This is the technology used in some COVID-19 vaccines. Doctors at Memorial Sloan Kettering Cancer Center are using this technology. They are making built vaccines for people with pancreatic cancer.Here is how the cancer vaccine works. Doctors first look at the makeup of the tumor in each patient. Then they design a vaccine based on the profile of the patients tumor. They make a vaccine for each patient, with cancer. The cancer vaccine is made for that patient.
In a small trial of 16 patients, the vaccine activated a strong immune response in half of them. For those patients, the results were remarkable — many of them lived six years longer than expected. The researchers said the immune response is very strong and it seems to last for a time.Think of it like this: you are teaching your bodys defense system, which’s your immune system to know the exact “fingerprint” of your cancer and then attack it by itself.This way of doing things is still being tried out with people but the results so far are really surprising and people are taking notice of the immune system and how it can help with cancer and the immune system.
Fighting Cancer With Electricity
There is also a brand-new device that the FDA recently approved for treating pancreatic cancer. Electrodes are attached to the patient’s skin over the abdomen, and the device sends high-frequency electrical signals directly to the cancer cells. These signals disrupt the cancer cells as they try to divide and multiply, helping to kill them. As a bonus, the electrical signals appear to also trigger the body’s immune system to join the fight — without adding the harsh chemicals that chemotherapy introduces into the body.
Doctors who have started using the device are hopeful it could give patients two to three more months of life, and with less pain than traditional options. While it is not a cure, every extra month is time spent with family, time to try the next new treatment, time for science to catch up.
If I Can Just Hold On a Little Longer
Vicky Stinson’s cancer eventually came back after her 13 months on daraxonrasib. It spread to her ovaries and is now at Stage 4. She has returned to chemotherapy, which has been harder on her body. But she has not given up. She is now helping researchers study her cancer’s genetic profile, hoping scientists can design something new specifically for her case.
Her story reflects the experience of thousands of pancreatic cancer patients who are racing against the clock — and for the first time in a long time, science seems to be racing with them.
Researchers believe that daraxonrasib will become the backbone of future treatments. Combined with vaccines, immune therapies, and devices like the electric-field machine, the goal is not just to slow the cancer down — but eventually, to cure it.For a disease that once offered almost no hope, 2026 feels like the beginning of something real.
Health
Is Your Doctor Using AI to Treat You Without Telling You

Picture this You walk into your doctor’s office, describe your symptoms, and while you’re sitting on that crinkly paper bed, your doctor pulls out their phone and quietly types something into an app. You assume they’re checking your chart. They’re not. They’re asking an AI.
This is happening in clinics and hospitals all across America right now. The tool is called OpenEvidence, and according to a recent NBC News investigation, about 65% of doctors in the United States are using it. That’s roughly 650,000 physicians. In April of this year alone, it showed up in nearly 27 million patient visits. Most patients never knew.
So What Is This Thing?
OpenEvidence is not your typical AI chatbot. It was built specifically for doctors and other healthcare professionals. Instead of pulling information from random corners of the internet, it searches through massive collections of real medical research — peer-reviewed studies, clinical guidelines, journal articles — and gives doctors a clear, organized answer fast.
Doctors sign up with their official government-issued healthcare ID number. When the students are inside they can ask the teacher many questions as they want about the lesson. The students can ask the teacher lots of questions. They can ask the teacher questions, about the lesson until they understand it.
The platform is based in Miami and was founded by a tech entrepreneur named Daniel Nadler. It’s backed by some heavy hitters in the investment world — Sequoia Capital, Google Ventures, Andreessen Horowitz, Nvidia, and Thrive Capital. A year ago, the company was worth around $1 billion. As of January 2026, that number had jumped to $12 billion. That kind of growth tells you how fast doctors have picked this up.
Why Are Doctors Reaching for It?
Doctors have always needed fast answers. For years, most of them used a service called UpToDate — long, detailed summaries of the latest research on just about every condition imaginable. It was reliable, but it wasn’t exactly quick. You had to know exactly what to search for, and even then, sifting through a lengthy article to find the one paragraph that actually answered your question took longer than most busy doctors had.
OpenEvidence works differently. A doctor can type a question the way they’d actually ask it out loud — something like, “my patient’s potassium just dropped and they’re on this medication, what do I do?” — and get a direct, relevant answer in seconds.
One doctor in New Hampshire used it when a patient’s potassium levels suddenly crashed. He needed to know fast whether it was a medication side effect or something more serious. OpenEvidence gave him a clear answer with treatment options right there on the spot.
A doctor working at a rural clinic in South Dakota was staring at an X-ray that might have shown a spinal fracture — or might not.He of recalled from medical school that some bone breaks do not appear clearly on X-rays so he asked OpenEvidence. It told him a CT scan would give a much more reliable answer and linked him to the studies that said so.
Dr. Paul Sax, an infectious disease specialist at Boston’s Brigham and Women’s Hospital, said that with older tools, hunting for specific answers was slow and clunky. With OpenEvidence, he described it as completely frictionless. You type what you actually want to know, and it finds it.
How Does It Stay Free?
Good question. The platform makes money through advertising. And here’s where things get a little uncomfortable — some of those ads come from pharmaceutical and medical device companies.
Most doctors who were interviewed said the ads are small, easy to ignore, and don’t get in the way of using the tool. But the fact remains: a platform that doctors use to make medical decisions is partly paid for by drug companies. That’s something worth knowing.
OpenEvidence also has licensing deals with some of the most respected medical journals on the planet, including the New England Journal of Medicine and JAMA, the Journal of the American Medical Association. That means when the tool generates an answer, it’s pulling from full research articles — not just abstracts or summaries — from the best sources in medicine.
Does It Get Things Right?
A lot of the time, yes. OpenEvidence reportedly scored a perfect 100% on the U.S. Medical Licensing Examination — the same test every doctor in the country has to pass. That’s a genuinely impressive result.
But here’s the thing. That exam covers standard medical knowledge. Real clinical practice is messier. A study published in December 2025 found that for more complicated, unusual medical questions — the kind that come up with rare diseases or tricky patient histories — OpenEvidence gave the correct answer less than 45% of the time. That study hasn’t been fully peer-reviewed yet, but it was enough to make a lot of researchers pay attention.
Experienced doctors say the tool handles everyday cases well. Where it stumbles is on the edge cases — the rare stuff that doesn’t come up often and where the research base is thin.
An emergency doctor in New York noticed it once overstated the liver risks of a certain medication in a patient whose real problem was heavy drinking. He came back weeks later and found the answer had been updated to be more accurate. But that kind of error, caught only because the doctor already knew enough to question it, is exactly what worries some people in the medical community.
What Are the Real Concerns Here?
The first is what this tool might do to younger doctors and medical students. Some physicians have noticed that newer doctors aren’t always building the same instincts that come from working through difficult cases on their own. When a tool does part of that thinking for you from the very start of your career, those muscles may never fully develop. One mid-career doctor in Missouri said it plainly — when you hand off part of a skill to a tool, you lose that part of the skill.
The second concern is that nobody has done a serious, large-scale study on how OpenEvidence is actually affecting patient outcomes. The tool developed quickly. Doctors and researchers are, on it now. They are still working to get results. The tool is moving ahead of what they can study. Doctors and researchers are trying hard to catch up.
Then there’s the privacy question. OpenEvidence says it follows HIPAA, the federal health privacy law. But not every hospital is convinced. Some have told their doctors not to enter any patient-specific information into the platform at all.
What Should You Take Away From This?
Your doctor using a tool like OpenEvidence isn’t necessarily a bad thing. Doctors have always looked things up. Medical knowledge moves fast, and no one can keep every study and guideline stored in their head.
But you have every right to know about it. If your doctor is consulting an AI tool during your appointment, that’s something you can ask about. A good doctor won’t have a problem explaining it.
The bigger picture is that AI is already inside the exam room, whether we’re talking about it or not. That conversation is worth having out loud.

Health Insurance, Mental Health & Healthcare: Why They’re All Connected

A New Hope for One of the Deadliest Cancers: Pancreatic Cancer Breakthroughs in 2026

Is Your Doctor Using AI to Treat You Without Telling You

Best Tips To Stay Fit In 2021

Facial Cupping

What are Some Advantages and Disadvantages of Herbal Tea?
-
 Fitness6 years ago
Best Tips To Stay Fit In 2021
-
 Health6 years ago
Facial Cupping
-
 Ayurveda6 years ago
What are Some Advantages and Disadvantages of Herbal Tea?
-

 Fitness6 years ago
Tips To Live A Healthy Life
-

 Fitness5 years ago
How Bean Bags Helping Yoga Better
-

 Fitness6 years ago
5 Bad Eating Habits That You Need To Avoid
-

 Fitness3 years ago
How To Raise Diastolic Blood Pressure Instantly – Stay Fit Healthy Lifestyle
-

 Fitness3 years ago
What Are The 10 Best Foods For A Diabetic Person